
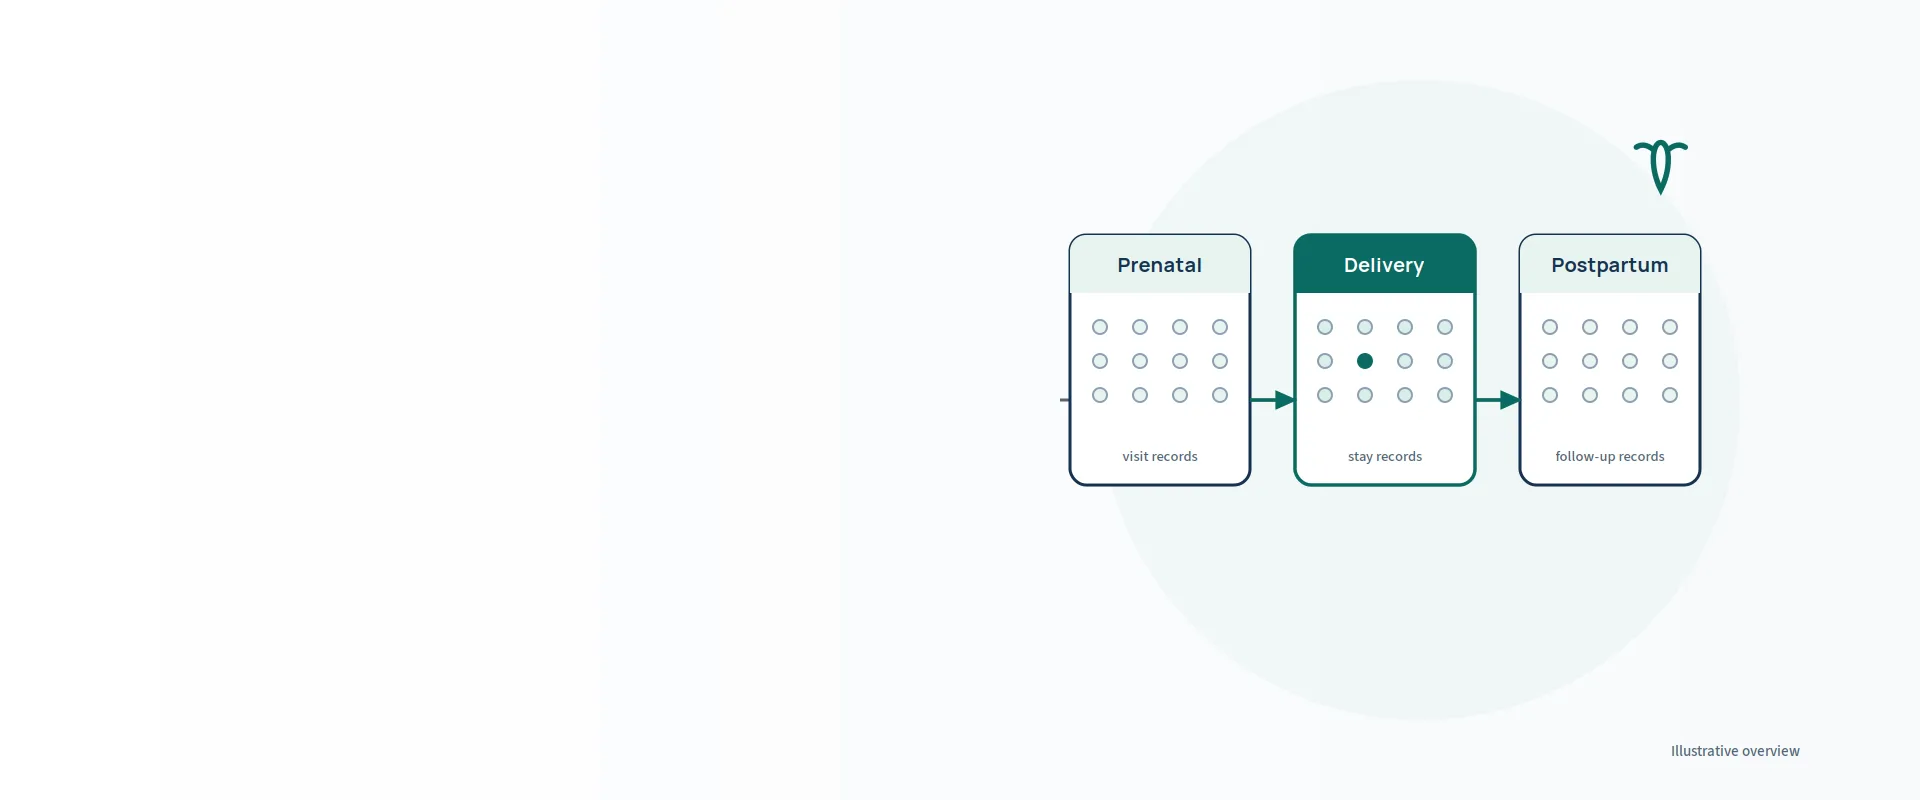
Medical Billing Services Group (MBSG) provides OB-GYN billing services built around this specialty’s toughest billing problems: where the maternity package begins and ends, how to bill when care transfers between physicians, and which services are separately supported. We work from the 2026 global-payment rules and are preparing for the new maternity care code set taking effect January 1, 2027.
Not sure your maternity claims will survive the 2027 code transition? Get a Free Billing Audit for a sample review of package-boundary errors, unbundling, and missed separately billable services.
Practice and setting fit
OB-GYN practices bill in two worlds at once: routine gynecology paid visit by visit, and maternity care paid through a package spanning months of antepartum visits, a delivery, and postpartum care. That split is what makes this specialty hard to bill, whether you are an independent group, hospital-employed, or high-risk practice.
The package breaks down in three situations. First, split care between physicians or groups, when a patient transfers late in pregnancy or a covering physician delivers. Each physician’s share must be identified, and payers handle split maternity care differently, so no single routine works for every plan. Second, separately supported services inside the maternity episode, such as ultrasounds, nonstress testing, or services at the point of delivery. Third, payer-by-payer transitions in 2026, as plans move from the global obstetric payment toward visit-based billing ahead of the 2027 code changes.
MBSG tracks each payer’s package boundaries, keeps documentation aligned to them, and makes sure separately supported work is captured. See our specialty billing services hub for other fields we support.
Documentation and coding risks
Documentation in OB-GYN must carry gestational detail every time: weeks of gestation, number of fetuses, trimester, and risk status. Diagnoses without gestational context are a leading reason maternity claims bounce. Transfer-of-care notes must record the date care changed hands, who assumed responsibility, and what was already performed.
Two sourced rules shape our maternity billing through the 2026 to 2027 transition:
Sourced example: billing antepartum visits as E/M during the 2026 transition
ACOG recommends health plans move from the global obstetric payment by billing antepartum visits with evaluation and management (E/M) codes, without visit limits or prior authorization, since E/M billing becomes the standard in 2027. Plans should make this shift no later than September 1, 2026 and append HCPCS modifier TH to mark the visit as maternity care. This is a recommendation to payers, not a mandate, so we confirm each plan’s policy before changing how your claims go out.
- Payer/program: guidance directed to health plans and payers (ACOG recommendation, not a mandate)
- Jurisdiction: United States
- Source title: “Payment for Obstetric Services” (ACOG coding library)
- Publication date: not displayed on the page (verified by text fetch)
- Effective date: new maternity care CPT codes effective January 1, 2027; ACOG-recommended payer transition no later than September 1, 2026
- Last reviewed: 2026-10-07
Sourced example: delivery-only codes and services billed separately near delivery
Per ACOG, the delivery-only codes cover labor management from admission to the unit, through delivery, and through completion of the postpartum orders and birth certificate. Services furnished at or near the point of delivery, including long-acting reversible contraception, should be billed separately rather than absorbed into the delivery payment. Point-of-delivery services need to be documented and claimed as their own lines, not assumed to be inside the package.
- Payer/program: guidance directed to health plans and payers (ACOG recommendation)
- Jurisdiction: United States
- Source title: “Payment for Obstetric Services” (ACOG coding library)
- Publication date: not displayed on the page (verified by text fetch)
- Effective date: new maternity care CPT codes effective January 1, 2027; ACOG-recommended payer transition no later than September 1, 2026
- Last reviewed: 2026-10-07
If the 2027 maternity code set will change how your practice gets paid, find out now what it will cost you. Request your free billing audit for an itemized review of your maternity claim sample, package-boundary findings, and a transition checklist.
Payer and authorization checks
Medicare is a minor payer for most OB-GYN practices, and its rules do not automatically apply to your commercial and Medicaid claims. This matters here because ACOG’s transition guidance is addressed to health plans as recommendations. A payer can move to E/M-based antepartum billing on its own timeline, attach its own modifiers, or stay on the global package into 2027, and your billing must follow each payer’s written policy.
Our payer checks confirm which plans adopted E/M antepartum billing and require modifier TH, verify split-care and transfer rules (which vary by plan and state Medicaid program), and watch authorization for high-cost items like advanced ultrasounds and fetal testing. Medicaid fee schedules and maternity bundles are state-specific.
Workflow and reporting
Our workflow is built around the maternity episode. Claims are scrubbed for package-boundary errors before submission: antepartum visits coded to each payer’s 2026 policy, split-care claims matching the documented episode division, and separately supported services near delivery claimed on their own lines. Eligibility is verified at intake and rechecked during long pregnancies, a common source of unpaid claims.
Reporting is monthly and actionable. Illustrative report examples include: payer-by-payer maternity claim aging, denial categories split between package-boundary and authorization denials, and split-care claims reconciled to documented transfer dates. These are illustrative examples, not guarantees. Our denial management team works late-caught maternity denials, and an independent medical billing audit is available for one-time deep reviews.
Onboarding and pricing factors
Onboarding starts with a documentation and contract review: your maternity coding routine, payer contracts, and a sample of split-care claims. You provide EHR access, payer enrollment records, and your fee schedule; we map every payer’s package rules, set up episode-level scrubbing, and confirm reporting cadence. Our medical coding services team keeps your coding aligned to each payer’s current policy.
Honest pricing factors for this specialty, with no invented rates:
- Pricing: maternity packages versus visit-based billing affect how work is priced, and we quote against your actual claim mix
- Minimum fees depend on monthly claim volume and provider count
- Turnaround: turnaround for claim submission and denial work is set in the agreement
- Staffing: team credentials are shared during scoping.
- all 50 states: service availability by state
- +1 (307) 396-4107 / contact@medicalbillingservicesgroup.com: contact details
See medical billing pricing, browse our billing resources, or contact us to start a conversation about your practice.
FAQs and dated sources
What is changing for OB billing in 2027?
The global obstetric codes are being deleted and a new maternity care code set takes effect January 1, 2027. ACOG recommends E/M codes become the standard for antepartum visits. (Source: ACOG “Payment for Obstetric Services”; verified 2026-10-07; effective January 1, 2027.)
How should antepartum visits be billed in 2026?
ACOG recommends plans use E/M codes for antepartum visits without limits or prior authorization, with modifier TH marking maternity care, transitioning no later than September 1, 2026. Confirm each payer’s policy first. (Source: ACOG “Payment for Obstetric Services”; verified 2026-10-07.)
When does the maternity package end?
Per ACOG’s payment guidance, delivery-only codes include labor management from admission to the unit through delivery and completion of the postpartum orders and birth certificate. Services at or near the point of delivery, such as long-acting reversible contraception, should be billed separately. (Source: ACOG “Payment for Obstetric Services”; verified 2026-10-07.)
What happens when a patient transfers care between physicians?
Split or transferred maternity care follows each payer’s own rules, which vary between commercial plans and state Medicaid programs. Document transfer dates and which physician performed each portion of care. We could not verify a single authoritative transfer rule from the sources checked, so we work from each payer’s written policy. (Gap logged below; reviewed 2026-10-07.)
Do Medicare maternity rules apply to my commercial and Medicaid claims?
No. Medicare’s rules do not automatically apply to Medicaid or commercial payers, and ACOG’s guidance is a recommendation to health plans, not a mandate. Verify each payer’s 2026 and 2027 maternity policy individually. (General payer-policy principle; reviewed 2026-10-07.)
Medical Billing Services Group (MBSG), Medical Billing & Revenue Cycle Management. If maternity package rules and the 2027 code transition are creating denials in your OB-GYN practice, start with a free billing audit for an itemized view of where your claims lose revenue.
General educational information, not legal advice or a guarantee of reimbursement. Requirements vary by payer, plan, setting and date of service. CPT is a registered trademark of the American Medical Association.